GLP-1 and Muscle Loss: What the Evidence Says
Yes, GLP-1 medications like semaglutide and tirzepatide can cause you to lose muscle alongside fat — but the research is clear that this is largely preventable with the right protein intake and resistance training.


Yes, GLP-1 medications like semaglutide and tirzepatide can cause you to lose muscle alongside fat — but the research is clear that this is largely preventable with the right protein intake and resistance training. The muscle loss is not some hidden catastrophe; it is a predictable consequence of rapid weight loss that you can actively work against. This question has moved from niche fitness forums into mainstream medicine fast, and for good reason: millions of people are now on these drugs without clear guidance on how to protect their body composition. If you want to dig into your own numbers — lean mass, metabolic markers, hormone levels — Vitals Vault labs can give you a baseline before or during treatment, and PocketMD is available if you want to talk through what you are seeing.
Why this is trending
A cluster of high-profile voices published GLP-1 muscle content at nearly the same time this week. Layne Norton, Gabrielle Lyon, and Mark Hyman each released videos questioning or contextualizing the muscle-loss narrative, while Renaissance Periodization's short arguing that most adults should take tirzepatide ignited a heated debate in strength-training communities about whether the drug's benefits outweigh its risks to muscle. What is genuinely new is not the concern itself — researchers have flagged lean mass loss in GLP-1 trials for years — but the scale of the conversation. With prescriptions in the tens of millions and growing, the question of what happens to your muscle is no longer academic. It is a practical issue for a huge number of people right now.
What GLP-1 Muscle Loss Actually Is
Weight loss always takes some muscle with it
When your body loses weight quickly — from any cause — it does not shed pure fat. A portion of what you lose is always lean tissue, including muscle, and GLP-1 drugs are no exception to this biological reality. The faster and larger the weight loss, the more lean tissue tends to go along for the ride.
GLP-1 trials show roughly 25–40% of lost weight is lean mass
Clinical trials of semaglutide and tirzepatide consistently show that somewhere between a quarter and four-tenths of the total weight lost comes from lean tissue rather than fat. That is not dramatically different from other aggressive weight-loss interventions, but it is significant enough to matter for your long-term strength, metabolism, and physical function.
Muscle loss is not the same as muscle damage
Losing some lean mass during a calorie deficit is different from the drug directly harming your muscle tissue — and that distinction matters. The evidence so far does not show that GLP-1 medications are toxic to muscle cells; rather, your body is simply drawing on available energy stores, and muscle is part of that pool when protein intake and training stimulus are low.
Lab testing
Track the markers that matter
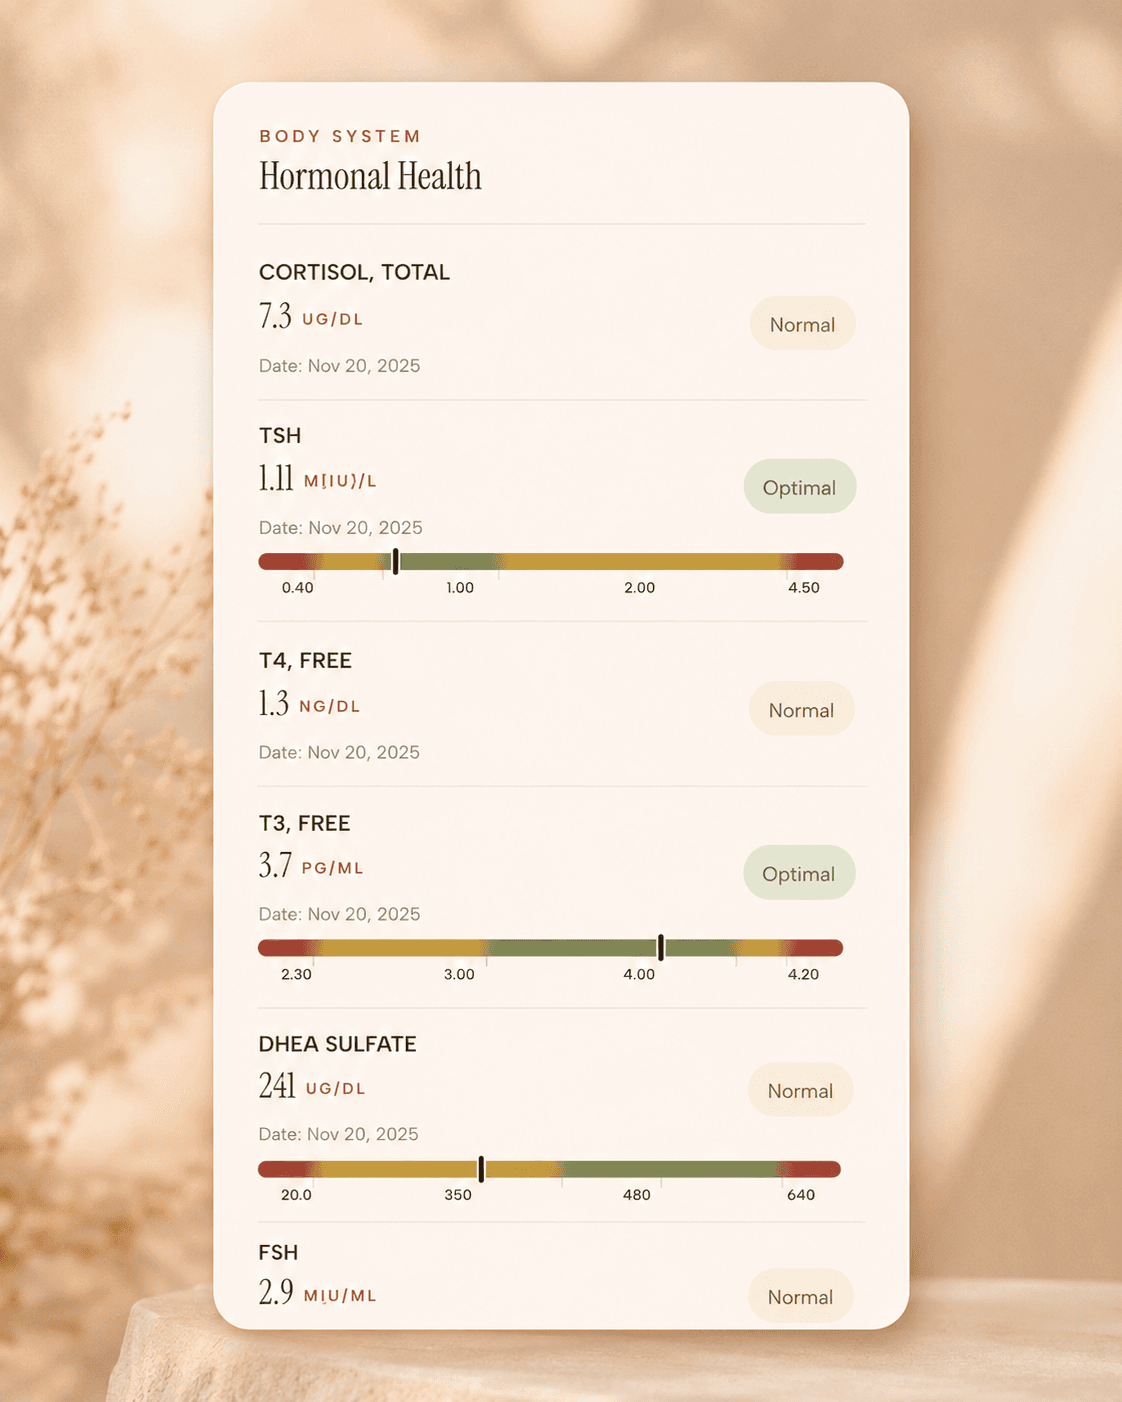
lean mass proxies, creatinine, albumin, testosterone, and more
with a starting-from-$99 panel covering 100+ tests, one visit, no insurance hassle
About 1 week
Schedule online — results typically within a week
Clear next steps
Guidance included, with follow-up care available
HSA / FSA
Eligible for pre-tax health spending accounts
Why Everyone Is Talking About This Now
Layne Norton and Gabrielle Lyon pushed back on the panic
Both researchers published content this week arguing that the muscle-loss risk from GLP-1s is real but manageable — and that the fitness community has been either catastrophizing it or ignoring it, depending on which corner of the internet you are in. Their core message is that the drug does not make muscle loss inevitable; your behavior around it does.
Renaissance Periodization's tirzepatide take divided the lifting world
A short video arguing that most adults should consider tirzepatide sparked genuine debate among people who have spent years optimizing their body composition without pharmaceutical help. The pushback was loud, but it also forced a more honest conversation about what the evidence actually shows versus what people fear.
Millions of users have no guidance on protecting muscle
The scale of GLP-1 prescriptions has outpaced the clinical infrastructure to support them, which means a large number of people are losing weight — and muscle — without anyone telling them what to do about it. That gap between prescription volume and practical guidance is exactly why this conversation is happening right now.
What the Evidence Actually Shows
STEP and SURMOUNT trials confirm lean mass loss
The large phase-3 trials for semaglutide (STEP program) and tirzepatide (SURMOUNT program) both measured body composition and found meaningful reductions in lean mass alongside fat loss. These are not small studies or cherry-picked results — they are the same trials that got these drugs approved, and the lean mass data was right there in the supplementary tables.
Resistance training dramatically changes the outcome
A growing body of research on calorie-restricted populations — including some GLP-1-specific data — shows that people who lift weights during weight loss preserve significantly more muscle than those who do not. The drug does not override the training signal; your muscles still respond to the mechanical load you put on them, even in a calorie deficit.
Higher protein intake is independently protective
Studies on weight loss consistently show that eating more protein — roughly 1.6 to 2.2 grams per kilogram of your target body weight per day — helps preserve lean mass during a deficit. On a GLP-1, where appetite suppression can make hitting protein targets feel difficult, this becomes an active challenge rather than a passive one.
The libido and hormone angle is underreported
Some GLP-1 users report drops in libido and energy that may be connected to changes in sex hormone levels during rapid weight loss — a side effect that does not get nearly as much attention as nausea or muscle loss. The evidence here is preliminary and largely anecdotal, but it is worth monitoring testosterone and related markers if you notice these changes.
How to Protect Your Muscle on GLP-1s
Prioritize protein even when you are not hungry
GLP-1 drugs suppress appetite so effectively that many users eat far too little protein without realizing it. You may need to treat protein as a deliberate target — front-loading it at meals, using shakes if solid food feels unappealing — rather than trusting hunger signals that the drug has essentially muted.
Lift weights at least twice a week, consistently
You do not need an elaborate program, but you do need progressive resistance training — exercises that challenge your muscles to work against a load — at a minimum of two sessions per week. Cardio alone will not preserve muscle during a significant calorie deficit, no matter how much of it you do.
Track your body composition, not just the scale
The number on the scale tells you almost nothing about whether you are losing fat or muscle, which is why tracking lean mass through DEXA scans, bioelectrical impedance, or lab proxies like creatinine and albumin gives you far more useful information. Knowing what you are actually losing lets you adjust your protein and training before the problem compounds.
Risks and Caveats Worth Knowing
Sarcopenia risk is higher in older adults
If you are over 60, you already lose muscle more easily than younger people — a process called age-related muscle loss (sarcopenia) — and adding a GLP-1-driven calorie deficit on top of that raises the stakes considerably. This does not mean the drugs are off-limits, but it does mean the protein and training recommendations are not optional for older users.
Stopping the drug without a plan can accelerate muscle loss
Some people who discontinue GLP-1 medications regain weight quickly, and if they have not built the muscle-preserving habits during treatment, the rebound can leave them with a worse body composition than when they started. The drug is a tool, not a permanent solution, and the habits you build while on it determine what happens when you come off it.
Hormone and libido changes deserve a real conversation with your doctor
Drops in libido, fatigue, or mood changes during GLP-1 treatment are not always just side effects of the drug itself — they can also reflect hormonal shifts from rapid weight loss, inadequate calorie intake, or disrupted sleep. If you are experiencing these symptoms, they are worth investigating with labs rather than dismissing as expected.
Frequently Asked Questions
How much muscle do you lose on Ozempic or tirzepatide?
Clinical trials suggest roughly 25 to 40 percent of the total weight lost on these drugs comes from lean tissue rather than fat, though the exact amount varies by individual. People who eat adequate protein and do resistance training consistently tend to lose significantly less muscle than those who do neither.
Can you prevent muscle loss on a GLP-1 completely?
Completely preventing lean mass loss during a large calorie deficit is very difficult regardless of the cause, but you can minimize it substantially. Hitting a protein target of around 1.6 to 2.2 grams per kilogram of your target body weight daily, combined with regular resistance training, is the most evidence-backed approach available.
Does GLP-1 muscle loss come back after you stop the drug?
If you regain weight after stopping a GLP-1 medication, some of what comes back will be fat rather than muscle — especially if you have not maintained training habits. Building and keeping muscle requires an ongoing stimulus, so the work you do during treatment is what determines your baseline when you come off it.
Why do some GLP-1 users report low libido or low energy?
Rapid weight loss from any cause can temporarily lower sex hormone levels, and eating too little — which is easy to do when appetite is suppressed — compounds that effect. If you are experiencing these symptoms, checking testosterone, thyroid, and nutritional markers through a blood panel is a reasonable first step before assuming it is the drug itself.
What labs should I check if I am on a GLP-1 and worried about muscle loss?
Useful markers include creatinine and albumin as rough proxies for lean mass, along with testosterone, thyroid hormones, and a complete metabolic panel to catch nutritional gaps. A Vitals Vault panel can cover all of these in a single visit, giving you a clear picture of what is actually happening in your body rather than guessing from symptoms alone.