Understanding Kidney Health testing
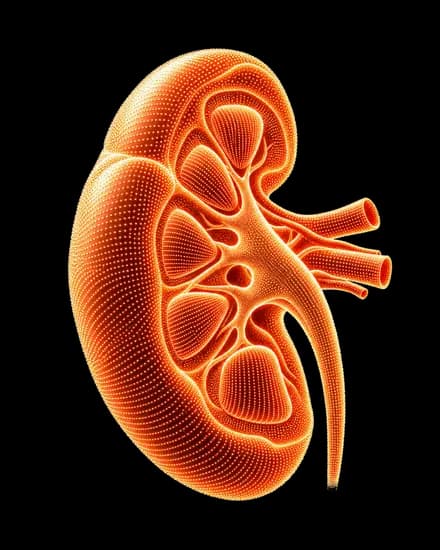
Your kidneys perform a feat of extraordinary precision: filtering approximately 200 litres of blood every day while selectively retaining what your body needs and excreting what it doesn't. They regulate blood pressure via the renin-angiotensin-aldosterone system, maintain the body's pH balance, control fluid volume, activate vitamin D, and signal the bone marrow to produce red blood cells through erythropoietin secretion. The kidneys are simultaneously a filtration organ, an endocrine gland, and a metabolic regulator.
Chronic kidney disease (CKD) affects approximately 850 million people worldwide — more than diabetes and cancer combined. The disease is characterised by its silence: most people have no symptoms until kidney function falls below 20–25% of normal, by which point fibrosis and structural damage are often irreversible. Blood-based markers — particularly eGFR, creatinine, cystatin C, and BUN — combined with urine albumin-to-creatinine ratio, provide a sensitive early warning system that enables intervention years before kidney function becomes clinically critical.
How Kidney connects across the body
Kidney health does not exist in isolation — it is deeply intertwined with every major system.
Cardiovascular System
The kidney-heart connection is bidirectional and powerful. Kidneys regulate blood pressure by controlling fluid volume and secreting renin, which drives angiotensin II production and aldosterone release. Hypertension damages glomerular capillaries over decades, progressing to CKD. Conversely, kidney disease elevates blood pressure through fluid retention and renin excess, creating a self-amplifying cycle. CKD is a more powerful independent risk factor for cardiovascular mortality than most traditional risk factors — at eGFR below 60, cardiovascular death risk doubles.
Bone & Mineral Metabolism
The kidneys activate vitamin D by converting 25(OH)D to its active form 1,25-dihydroxyvitamin D (calcitriol), which drives intestinal calcium absorption. As CKD progresses, calcitriol production declines, causing hypocalcaemia. The parathyroid glands respond by secreting more PTH (secondary hyperparathyroidism), which leaches calcium from bone to normalise blood levels — a process called renal osteodystrophy. Elevated phosphate (as kidneys fail to excrete it) accelerates vascular calcification, further increasing cardiovascular risk in CKD.
Red Blood Cell Production
Peritubular cells in the kidney cortex are the primary site of erythropoietin synthesis. EPO secretion rises in response to hypoxia (low oxygen delivery) and drives red cell production in bone marrow. In CKD, both reduced EPO secretion and the toxic effects of uraemic compounds on bone marrow cause normochromic normocytic anaemia that worsens with disease progression. The resulting fatigue and reduced exercise tolerance further accelerate cardiovascular deconditioning in CKD patients.
Electrolyte & Acid-Base Balance
The kidneys maintain serum potassium within the narrow 3.5–5.0 mEq/L range that cardiac muscle requires for normal rhythm. In CKD, potassium excretion declines — hyperkalaemia (elevated potassium) can trigger fatal arrhythmias. The kidneys also excrete acid daily to maintain blood pH at 7.35–7.45; declining filtration capacity causes metabolic acidosis. Even mild metabolic acidosis (bicarbonate below 22 mEq/L) accelerates muscle wasting, impairs insulin signalling, and worsens bone demineralisation. Correcting acidosis with bicarbonate supplementation slows CKD progression in trials.
Supporting Kidney health
Nutrition
- Maintain adequate hydration — chronic mild dehydration concentrates urine and increases risk of kidney stones and UTIs. Aim for pale yellow urine as a practical hydration indicator.
- In CKD, reduce dietary sodium to below 2,000mg per day to lower blood pressure and reduce proteinuria — the primary modifiable driver of CKD progression.
- Moderate dietary protein (0.6–0.8g/kg/day) in established CKD reduces uraemic load; however, adequate protein is essential in healthy individuals — protein restriction before CKD diagnosis is not warranted.
- Increase dietary potassium through fruits and vegetables in healthy individuals — plant-based potassium is associated with lower blood pressure and reduced CKD incidence.
Medical Risk Management
- Control blood pressure aggressively — RAAS inhibitors (ACE inhibitors and ARBs) reduce intraglomerular pressure and proteinuria, slowing CKD progression beyond their blood-pressure-lowering effects.
- Manage blood glucose tightly in diabetes — HbA1c below 7% significantly reduces the rate of diabetic nephropathy progression.
- Avoid NSAIDs (ibuprofen, naproxen) chronically — they reduce renal blood flow and can cause acute kidney injury, particularly in people with existing CKD or mild dehydration.
Exercise
- Regular aerobic exercise reduces blood pressure and improves GFR in early-stage CKD, as well as improving cardiovascular outcomes.
- Resistance training is safe and beneficial in CKD — concerns about protein catabolism raising creatinine are theoretical; the cardiovascular and metabolic benefits outweigh them.
Clinical note
eGFR estimation using the CKD-EPI equation has limitations in people with very high or very low muscle mass, as creatinine reflects both filtration and muscle turnover. Cystatin C is a creatinine-independent eGFR estimator that is more accurate across body compositions. When eGFR is borderline or risk factors are present, a urine albumin-to-creatinine ratio (UACR) should always be measured alongside blood markers for complete kidney health assessment.