Psychedelic Therapy: Mental Health Beyond Symptoms
Psychedelic therapy is not about getting high — it is about giving your brain a rare window to rewire itself, and a growing body of clinical evidence suggests it may do something that decades of antidepressants have struggled to achieve: move people from merely surviving to genuinely thriving.


Psychedelic therapy is not about getting high — it is about giving your brain a rare window to rewire itself, and a growing body of clinical evidence suggests it may do something that decades of antidepressants have struggled to achieve: move people from merely surviving to genuinely thriving. That distinction matters more than it sounds, because suppressing symptoms and restoring full mental health are not the same thing. The conversation around this has shifted meaningfully in the last few months, as leading psychiatrists and researchers have started arguing publicly that the standard model of mental health care sets the bar too low. If you have been curious about where psychedelic therapy fits into your own mental health picture — or skeptical about whether the hype is real — it is worth understanding what the science actually says, what is still uncertain, and how hormones fit into the picture in ways most people never hear about. Vitals Vault's lab panels can help you understand your own hormonal baseline, and PocketMD is available if you want to talk through what any of this means for you personally.
Why this is trending
Two high-profile conversations landed almost simultaneously this week. Psychiatrist Linus Abrams joined Peter Attia to make the case that mental health treatment has been too narrowly focused on neurotransmitters — particularly serotonin — while largely ignoring the role of hormones like testosterone, estrogen, and cortisol in shaping mood, cognition, and resilience. Around the same time, sleep researcher Matt Walker dedicated an episode to the emerging science of psychedelics, covering what clinical trials are actually showing about psilocybin and MDMA. Together, these conversations crystallized something that has been building in academic psychiatry for a while: the goal of treatment should be flourishing, not just the absence of symptoms. This is not a fringe position anymore. The FDA has been reviewing MDMA-assisted therapy for PTSD, psilocybin has received Breakthrough Therapy designation for treatment-resistant depression, and major research centers at Johns Hopkins, NYU, and Imperial College London are publishing peer-reviewed trial data. The influencer moment is real, but it is landing on top of a genuine scientific shift — which is exactly why it is worth paying careful attention rather than dismissing it or uncritically embracing it.
What psychedelic-assisted therapy actually is
A guided experience, not a recreational one
In clinical settings, psychedelic therapy means taking a carefully measured dose of a substance — most commonly psilocybin or MDMA — in the presence of trained therapists, in a calm and structured environment. The drug is not the treatment by itself; the psychological work that happens during and after the experience is where the therapeutic value comes from.
The brain becomes unusually open to change
Psilocybin temporarily disrupts the brain's default mode network [DMN] — the mental autopilot responsible for your sense of self and your habitual thought patterns. This disruption appears to create a window of heightened neuroplasticity, meaning your brain is more capable of forming new connections and breaking old ones than it normally would be.
The goal is flourishing, not just symptom relief
The emerging framework in clinical psychiatry draws a sharp line between reducing symptoms — feeling less depressed — and restoring full functioning, meaning energy, purpose, connection, and joy. Psychedelic therapy is being studied specifically because early trial data suggests it may move people further along that spectrum than conventional treatments alone.
Lab testing
Your hormones
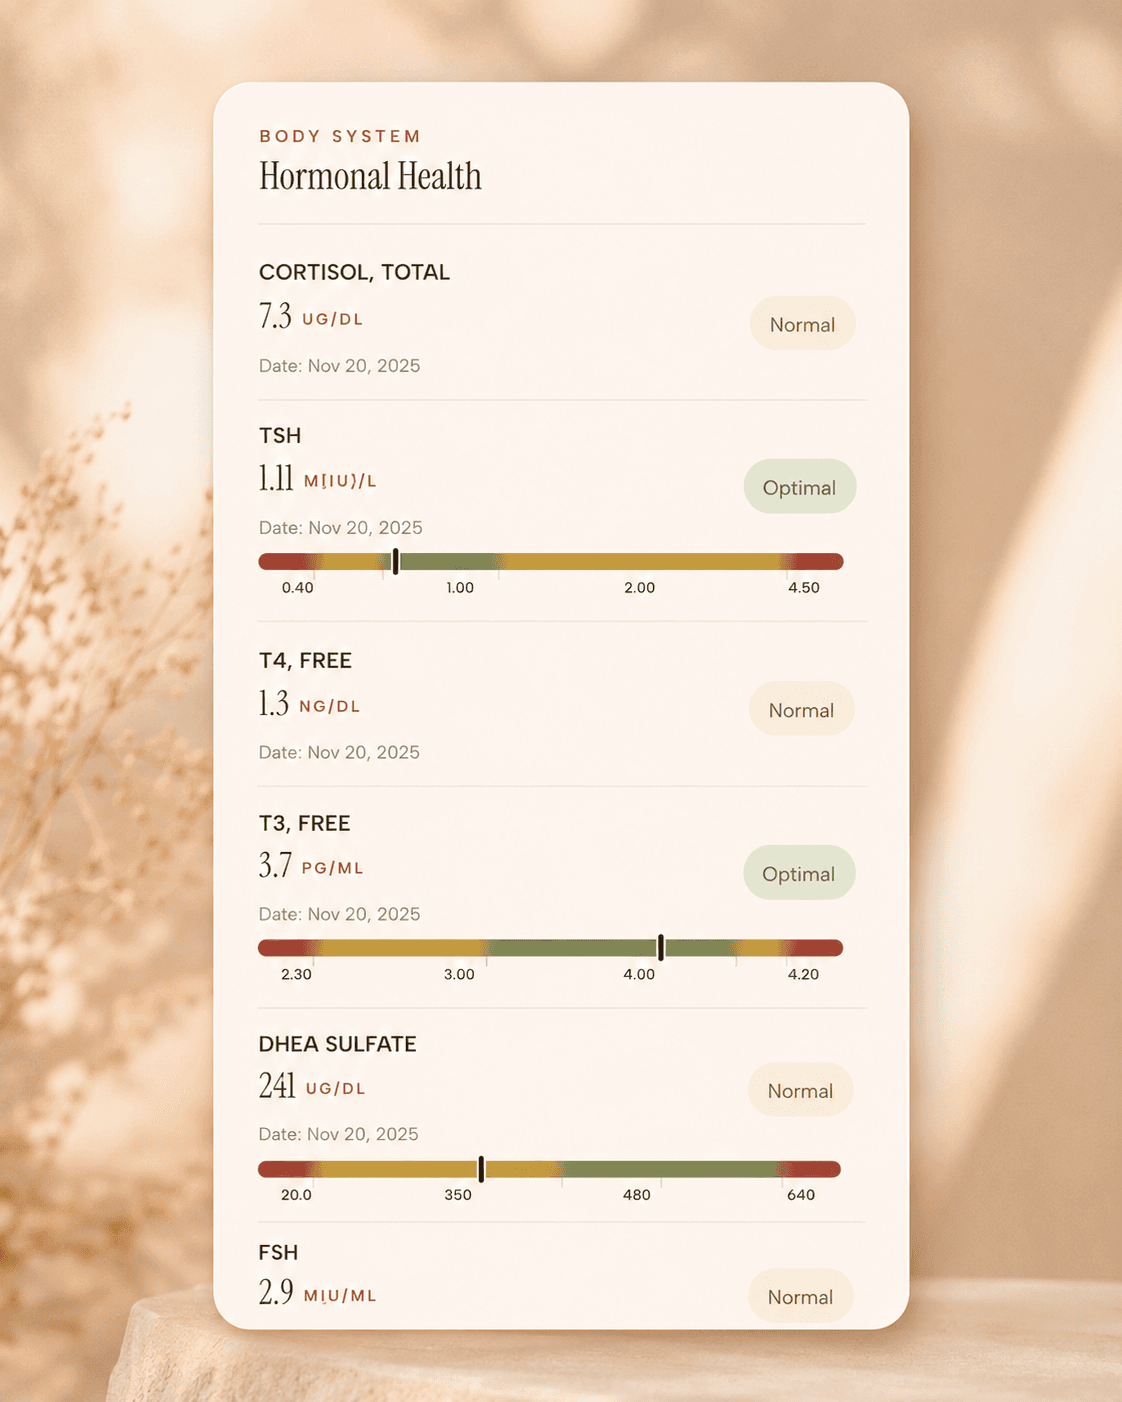
testosterone, estrogen, cortisol, thyroid
have a direct impact on mood and resilience that most psychiatrists never check. The Vitals Vault starting-from-$99 panel covers 100+ tests in one visit, so you can see exactly where your levels stand
About 1 week
Schedule online — results typically within a week
Clear next steps
Guidance included, with follow-up care available
HSA / FSA
Eligible for pre-tax health spending accounts
Why this conversation is happening right now
Conventional treatments leave many people stuck
Roughly one in three people with major depression does not respond adequately to standard antidepressants, and many who do respond still describe feeling blunted rather than well. That gap between partial treatment and genuine recovery has created real demand for alternatives, and psychedelic research is one of the few areas producing genuinely promising data.
Clinical trial results are hard to ignore
A landmark Johns Hopkins trial found that two doses of psilocybin produced significant reductions in depression scores that lasted months — results that outperformed many antidepressant studies. MDMA-assisted therapy for post-traumatic stress disorder [PTSD] showed similarly striking results in Phase 3 trials, with a large proportion of participants no longer meeting the diagnostic criteria for PTSD after treatment.
Psychiatry is reckoning with what it missed
The neurotransmitter model — the idea that depression is essentially a serotonin deficiency — has been quietly losing scientific support for years, and leading psychiatrists are now saying so publicly. The newer view is that mental health is shaped by a much wider system that includes hormones, inflammation, sleep quality, and social connection, which is why treatments that only target serotonin so often fall short.
What the clinical trials are actually showing
Psilocybin for depression: real but early
Multiple randomized controlled trials have now shown that psilocybin produces meaningful reductions in depression, including in people who have not responded to other treatments. The effects appear to last weeks to months after just one or two sessions, which is unusual for any psychiatric intervention — but researchers are still working out who responds best and why.
MDMA for PTSD: the most advanced pipeline
MDMA-assisted therapy has the most mature clinical data of any psychedelic treatment, with Phase 3 trials showing that a significant majority of participants experienced dramatic symptom reduction. The FDA's review process has been complicated by concerns about trial methodology and therapist conduct, which is a reminder that even promising science requires rigorous oversight.
Ketamine: already here, already complex
Ketamine and its derivative esketamine are already FDA-approved for treatment-resistant depression, which makes them the most accessible psychedelic-adjacent treatment available right now. They work differently from psilocybin — primarily through the glutamate system rather than serotonin — and the antidepressant effect can be rapid but often requires repeated infusions to maintain.
What the trials cannot yet tell you
Most trials have been conducted in carefully screened populations under highly controlled conditions, which means the results may not translate directly to real-world clinical practice. Long-term safety data beyond one to two years is still limited, and researchers do not yet have reliable ways to predict who will benefit most or how to handle non-responders.
The hormone connection psychiatry has been overlooking
Low testosterone affects mood in men and women
Testosterone is not just a sex hormone — it plays a direct role in motivation, emotional resilience, and the ability to experience pleasure [anhedonia]. Men and women with low testosterone often describe symptoms that look exactly like depression, and those symptoms frequently do not respond well to antidepressants because the underlying hormonal driver is never addressed.
Estrogen shapes how your brain handles stress
Estrogen has a significant influence on serotonin receptors and on the stress response system [HPA axis], which is why mood often becomes much harder to regulate during perimenopause and menopause. Treating depression in a woman with declining estrogen without considering hormone levels is, as some psychiatrists now put it, like trying to fill a leaking bucket.
Cortisol and chronic stress rewire the brain over time
Chronically elevated cortisol — the stress hormone — physically shrinks the part of your brain involved in memory and emotional regulation [hippocampus], and that structural change contributes to depression and anxiety. This is one reason why psychedelic therapy's apparent ability to promote neuroplasticity is so interesting to researchers: it may help reverse some of that stress-related damage.
What you need to know before getting excited
These are not treatments you can safely self-administer
The positive trial results come from settings with trained therapists, medical screening, and careful follow-up — not from recreational use or unguided home sessions. People with a personal or family history of psychosis or bipolar disorder face real risks of triggering serious psychiatric episodes, and that screening process exists for good reason.
The legal landscape is still a patchwork
Psilocybin is legal for therapeutic use in Oregon and Colorado, and a small number of other jurisdictions, but it remains a Schedule I controlled substance federally in the United States. MDMA-assisted therapy is not yet FDA-approved, and ketamine clinics vary enormously in quality and oversight — so if you are exploring options, the setting and the practitioners matter as much as the substance.
Symptom relief and full recovery are still not guaranteed
Even in the most successful trials, a meaningful proportion of participants did not respond, and some experienced temporary increases in anxiety or emotional distress during the experience. Psychedelic therapy is a promising tool, not a cure, and the researchers leading this field are careful to say so — which is worth keeping in mind when you encounter more breathless coverage elsewhere.
Frequently Asked Questions
Is psilocybin therapy legal and available where I live?
Psilocybin-assisted therapy is currently legal for supervised therapeutic use in Oregon and Colorado, and a handful of other jurisdictions are moving in that direction. Federally in the US it remains a Schedule I substance, so availability depends heavily on where you live and what kind of program you are looking at. If you are seriously exploring this, a physician can help you understand what is actually accessible and legitimate in your area.
Can psychedelic therapy replace antidepressants?
The clinical trials are not designed as head-to-head replacements, and researchers are careful not to frame it that way. What the evidence suggests is that psychedelic therapy may work for people who have not responded to antidepressants, or may produce deeper and more lasting change in some cases — but stopping any psychiatric medication should always be done with your prescribing doctor, not based on a trend.
How do hormones connect to depression and anxiety?
Hormones like testosterone, estrogen, and cortisol directly influence the brain systems that regulate mood, motivation, and stress response. Low testosterone can cause symptoms that look identical to depression, and declining estrogen during perimenopause can make the brain's stress response much harder to manage. Getting your hormone levels tested is one of the most overlooked first steps in understanding why standard treatments sometimes fall short.
What is the difference between ketamine and psilocybin therapy?
Ketamine works primarily through the glutamate system and produces a dissociative effect rather than a classic psychedelic experience — it is already FDA-approved for treatment-resistant depression and is available through licensed clinics now. Psilocybin works through serotonin receptors and produces a more immersive, emotionally rich experience that is typically done in one or two longer sessions with a therapist. Both show promise, but they work differently and suit different situations.
Who should not consider psychedelic therapy?
People with a personal or family history of schizophrenia, psychosis, or bipolar disorder with psychotic features face a meaningfully elevated risk of serious adverse effects and are generally excluded from clinical trials for this reason. Cardiovascular conditions, certain medications, and pregnancy are also important factors that require medical evaluation before any psychedelic treatment. This is exactly the kind of conversation that benefits from talking to a physician who knows your full health picture.