Why Menopause Wrecks Sleep—and How to Fix It
Yes, menopause genuinely wrecks sleep — and it does so through a specific hormonal cascade that standard sleeping pills were never designed to address.



Yes, menopause genuinely wrecks sleep — and it does so through a specific hormonal cascade that standard sleeping pills were never designed to address. The 3 AM wake-up, the drenched sheets, the lying awake with a racing mind: these are not signs that something is wrong with you personally. They are predictable consequences of falling estrogen and progesterone levels reshuffling the way your brain regulates temperature, stress hormones, and sleep architecture. The good news is that researchers now understand this mechanism well enough to offer real solutions — from light exposure timing and meal windows to hormone therapy — and the evidence behind each one is clearer than it has ever been. If you want to dig into your own hormone picture before or alongside any of these strategies, Vitals Vault's lab panels and PocketMD telehealth line can help you get baseline numbers and talk through options with a clinician.
Why this is trending
Sleep specialist Dr. Kristen Holmes joined OB-GYN and menopause advocate Dr. Mary Claire Haver this week for a full-length episode on what she calls a "menopause sleep reset," and Dr. Haver followed it with three short-form videos on the same theme — including one specifically on why sleeping pills fail menopausal women. That volume of content from credible clinical voices in a single week signals that the audience is hungry for answers, not reassurance. What is genuinely new here is not the problem itself but the framing: researchers and clinicians are now treating menopause-related insomnia as a distinct physiological condition rather than a generic sleep complaint, which changes both the diagnostic approach and the treatment options worth considering.
What's Actually Happening to Your Sleep
Estrogen loss destabilizes your body's thermostat
The part of your brain that controls body temperature (hypothalamus) relies on estrogen to stay calibrated, and when estrogen drops, it becomes hypersensitive to tiny shifts in core temperature. That hypersensitivity triggers a hot flash or night sweat — essentially a false alarm that jolts you out of deep sleep — and because your core temperature then has to recover, falling back asleep can take 30 to 60 minutes even after the flush itself is gone.
Progesterone was your natural sleep aid, and now it's gone
Progesterone acts on the same brain receptors that sedatives target, which is why many women sleep deeply during the luteal phase of their cycle and then notice lighter, more fragmented sleep as progesterone declines in perimenopause. Losing this hormone does not just make sleep feel lighter — it measurably reduces the amount of slow-wave deep sleep your brain achieves each night, which is the stage most responsible for physical recovery and memory consolidation.
Cortisol timing shifts, and 3 AM becomes a problem
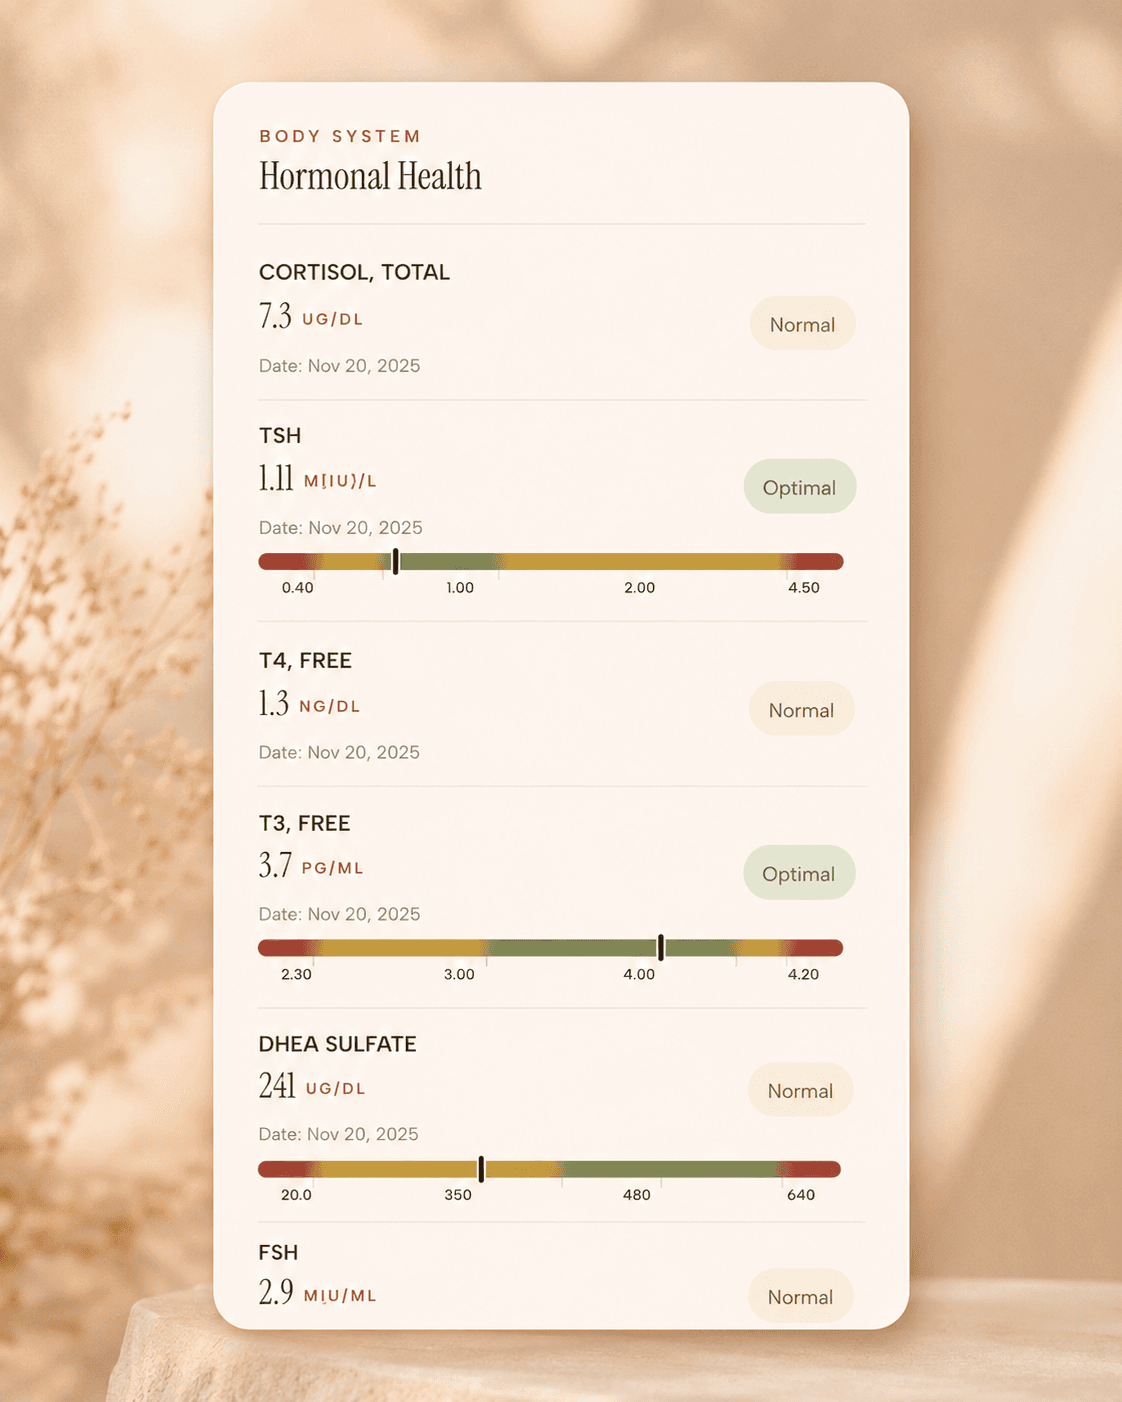
In a healthy sleep cycle, the stress hormone cortisol stays low through the night and rises gradually toward morning to help you wake up. During menopause, that cortisol curve can shift earlier, spiking in the early morning hours and pulling you out of sleep at 3 or 4 AM with a wired, anxious feeling that has no obvious cause. This is not anxiety disorder — it is a hormonal timing problem, and treating it as pure insomnia with sedatives does not fix the underlying rhythm.
Lab testing
Estrogen, progesterone, FSH, cortisol, and thyroid markers can all influence sleep quality during perimenopause and menopause. The Vitals Vault starting-from-$99 panel covers 100+ tests in one visit
no referral needed
About 1 week
Schedule online — results typically within a week
Clear next steps
Guidance included, with follow-up care available
HSA / FSA
Eligible for pre-tax health spending accounts
Why Everyone Is Talking About This Now
Clinicians are reframing this as a distinct condition
For decades, menopause-related insomnia was lumped in with general sleep complaints and treated with the same tools — sleep hygiene advice, antihistamine-based sleep aids, or benzodiazepines. A growing body of research and a new generation of menopause-specialist physicians are pushing back on that, arguing that hormonal insomnia has a specific mechanism that requires targeted solutions rather than generic sedation.
Sleeping pills are getting called out for not working here
Standard over-the-counter sleep aids work primarily by making you drowsy, but they do not restore the deep-sleep architecture that falling progesterone disrupts, and they do nothing for the temperature dysregulation driving night sweats. Several clinicians have now said this publicly and plainly, which is landing with women who have tried these products and found them ineffective or left them feeling groggy without actually sleeping better.
Wearable data is making the problem visible
Women who track sleep with rings or watches are now arriving at conversations with their doctors holding months of data showing exactly how fragmented their sleep is — and that data is harder to dismiss than a subjective complaint. This is accelerating both the clinical conversation and the public interest in understanding what is actually causing the disruption.
What the Evidence Actually Shows
Hormone therapy has the strongest sleep evidence
Estrogen therapy — with or without progesterone, depending on whether you have a uterus — has the most consistent evidence for improving menopause-related sleep disruption, primarily by reducing the hot flashes and night sweats that fragment sleep. Micronized progesterone in particular has shown sleep-promoting effects in clinical trials beyond just hot flash reduction, likely because of its direct action on calming brain receptors.
Light exposure timing genuinely shifts your sleep clock
Getting bright light — ideally sunlight — within 30 to 60 minutes of waking helps anchor your body's internal clock (circadian rhythm) and can improve both sleep onset and early-morning waking over time. This is not a wellness platitude; it is one of the most replicated findings in sleep science, and it is particularly relevant during menopause because estrogen loss makes the circadian system less robust and more vulnerable to drift.
Meal timing affects core temperature and sleep quality
Eating a large meal within two to three hours of bedtime raises your core body temperature during digestion, which directly competes with the temperature drop your body needs to initiate and maintain deep sleep — and that temperature drop is already harder to achieve when estrogen is low. Shifting the bulk of your calories earlier in the day is one of the lower-effort changes with a meaningful effect on sleep quality, particularly for women who are also dealing with night sweats.
Cognitive behavioral therapy for insomnia outperforms pills long-term
Cognitive behavioral therapy for insomnia (CBT-I) — a structured program that addresses the thoughts and behaviors that perpetuate poor sleep — has been shown in multiple trials to produce better long-term outcomes than sedative medication, including in perimenopausal and postmenopausal women. It is not a quick fix; it typically takes four to eight weeks to see full benefit, but unlike medication, the gains tend to persist after the program ends.
Changes You Can Actually Start This Week
Build a consistent anchor for your sleep clock
Pick a wake time and hold it every day — including weekends — because consistency is what trains your brain to release melatonin at the right time in the evening. Pair that with morning light exposure and, if possible, a short outdoor walk, which combines light, movement, and a drop in cortisol in a way that stacks benefits without adding complexity to your day.
Track your triggers before you overhaul everything
Keeping a simple log of when night sweats or wake-ups happen — and what you ate, drank, or felt in the two hours before bed — often reveals personal triggers within a week or two. Alcohol is a particularly common culprit because it suppresses deep sleep and raises core body temperature in the second half of the night, which is exactly when menopausal women are already most vulnerable to waking.
Have the hormone therapy conversation with real information
If lifestyle changes are not enough, hormone therapy is worth a genuine conversation with a clinician who is current on the evidence — not a reflexive dismissal based on outdated risk framing from the early 2000s. The decision depends on your personal health history, your symptom burden, and your preferences, which is exactly the kind of nuanced conversation that benefits from a clinician who specializes in this area rather than a general practitioner who sees menopause rarely.
What to Know Before You Try Anything
Not every 3 AM wake-up is hormonal
Thyroid problems, sleep apnea, anxiety disorders, and certain medications can all produce symptoms that look and feel identical to menopause-related insomnia, so it is worth ruling those out — especially if you have not had thyroid or sleep screening recently. A clinician can help you figure out whether what you are experiencing is primarily hormonal or whether something else is driving it.
Hormone therapy is not right for everyone
Women with a personal history of certain hormone-sensitive cancers, unexplained vaginal bleeding, or active cardiovascular disease are generally not candidates for systemic estrogen therapy, and the risk-benefit calculation is different for everyone. This is a decision to make with a clinician who knows your full history — not something to self-prescribe based on what worked for someone else.
CBT-I requires effort, and that is worth knowing upfront
Cognitive behavioral therapy for insomnia often involves a period of deliberate sleep restriction early in the program, which can feel worse before it gets better — and that surprises people who expect it to be gentle. Going in with realistic expectations makes it much more likely you will stick with it long enough to see the results the evidence supports.
Frequently Asked Questions
Why do I keep waking up at 3 AM during perimenopause?
The most common reason is a shift in your cortisol curve — the stress hormone that normally rises gradually toward morning can start spiking earlier during perimenopause, pulling you out of sleep in the early hours with a wired or anxious feeling. Night sweats from temperature dysregulation can also cause these wake-ups, and the two often happen together. Tracking whether you wake up hot and sweaty versus alert and anxious can help you and your clinician figure out which mechanism is dominant for you.
Why don't sleeping pills work for menopause sleep problems?
Most sleeping pills work by making you drowsy, but they do not restore the deep-sleep architecture that declining progesterone disrupts, and they have no effect on the hot flashes and night sweats that are physically waking you up. You may fall asleep faster but still wake at 3 AM drenched in sweat, because the underlying hormonal problem is untouched. Treatments that address the root cause — whether hormone therapy, CBT-I, or targeted lifestyle changes — tend to produce more meaningful and lasting improvement.
Does hormone therapy actually improve sleep during menopause?
Yes, and it has some of the strongest evidence of any intervention for menopause-related sleep disruption, primarily because it reduces the hot flashes and night sweats that fragment sleep. Micronized progesterone also appears to have a direct calming effect on the brain that can improve sleep quality beyond just temperature control. Whether hormone therapy is appropriate for you depends on your personal health history, so this is a conversation worth having with a menopause-informed clinician.
What is CBT-I and does it work for menopause insomnia?
Cognitive behavioral therapy for insomnia (CBT-I) is a structured program — typically four to eight sessions — that identifies and changes the thought patterns and behaviors that keep insomnia going, such as spending too long in bed awake or catastrophizing about sleep loss. Clinical trials have shown it outperforms sleeping pills for long-term outcomes, and studies in perimenopausal and postmenopausal women specifically have found meaningful improvements in sleep quality. It takes effort and a willingness to feel temporarily worse before you feel better, but the results tend to last.
Can what I eat and when I eat it really affect menopause sleep?
Yes, and the mechanism is straightforward: digesting a large meal raises your core body temperature, which directly interferes with the temperature drop your body needs to enter and maintain deep sleep — a drop that is already harder to achieve when estrogen is low. Alcohol is particularly disruptive because it suppresses deep sleep and causes a rebound arousal in the second half of the night, which is when menopausal women are already most vulnerable. Shifting your main meal earlier and keeping the two hours before bed light tends to make a noticeable difference within a week or two.