What Estrogen Decline Really Does to Your Body
Estrogen decline is not just a hot flash problem.



Estrogen decline is not just a hot flash problem. It is a whole-body event that touches your heart, your brain, your bones, your muscles, and the way your metabolism handles food and fat — and for most women, it begins years before the last period. The conversation in medicine has shifted from managing uncomfortable symptoms to preventing serious disease, and that shift matters for every woman in her 30s, 40s, and beyond. If you have been trying to make sense of the research — or wondering whether what you are feeling is hormonal — a good place to start is understanding what estrogen actually does when it is present, so you can understand what happens when it leaves. Vitals Vault's hormone panels and PocketMD telehealth line exist precisely for moments like this, when you need real answers rather than a waiting room.
Why this is trending
Dr. Mary Claire Haver, one of the most-followed OB-GYNs on social media, recently posed a pointed question: what if men lost testosterone at midlife the way women lose estrogen? The analogy is deliberate. Testosterone loss in men is treated as a medical event worthy of monitoring, intervention, and research funding. Estrogen loss in women has historically been framed as a natural transition to be endured. That framing is being challenged loudly and with growing clinical backing. At the same time, Dr. Gabrielle Lyon and others in the muscle-health space have been drawing attention to the joint pain, muscle weakness, and body composition changes that hit women in perimenopause — symptoms that rarely get connected to hormones in a standard doctor's visit. The result is a wave of women asking better questions, and a medical community that is slowly catching up.
What Estrogen Decline Actually Is
A gradual process, not a single event
Estrogen does not simply switch off at menopause. Levels begin fluctuating and trending downward during perimenopause, which can start in a woman's late 30s or early 40s — sometimes a decade before periods stop. This means the biological effects of declining estrogen are already accumulating long before most women or their doctors start paying attention.
Estrogen is a systemic hormone, not a reproductive one
Most people think of estrogen as a sex hormone, but it functions more like a maintenance signal for the entire body. Receptors for estrogen exist in your brain, your heart muscle, your blood vessels, your bones, your skin, and your gut — which is why its decline produces effects that seem completely unrelated to reproduction.
Three forms, and the one that matters most at midlife
Your body makes three forms of estrogen: estrone, estradiol, and estriol. Estradiol [17β-estradiol] is the most biologically active form during your reproductive years and the one that drops most sharply at menopause. After menopause, estrone — made partly in fat tissue — becomes the dominant form, but at levels too low to maintain the protective effects estradiol provided.
Lab testing
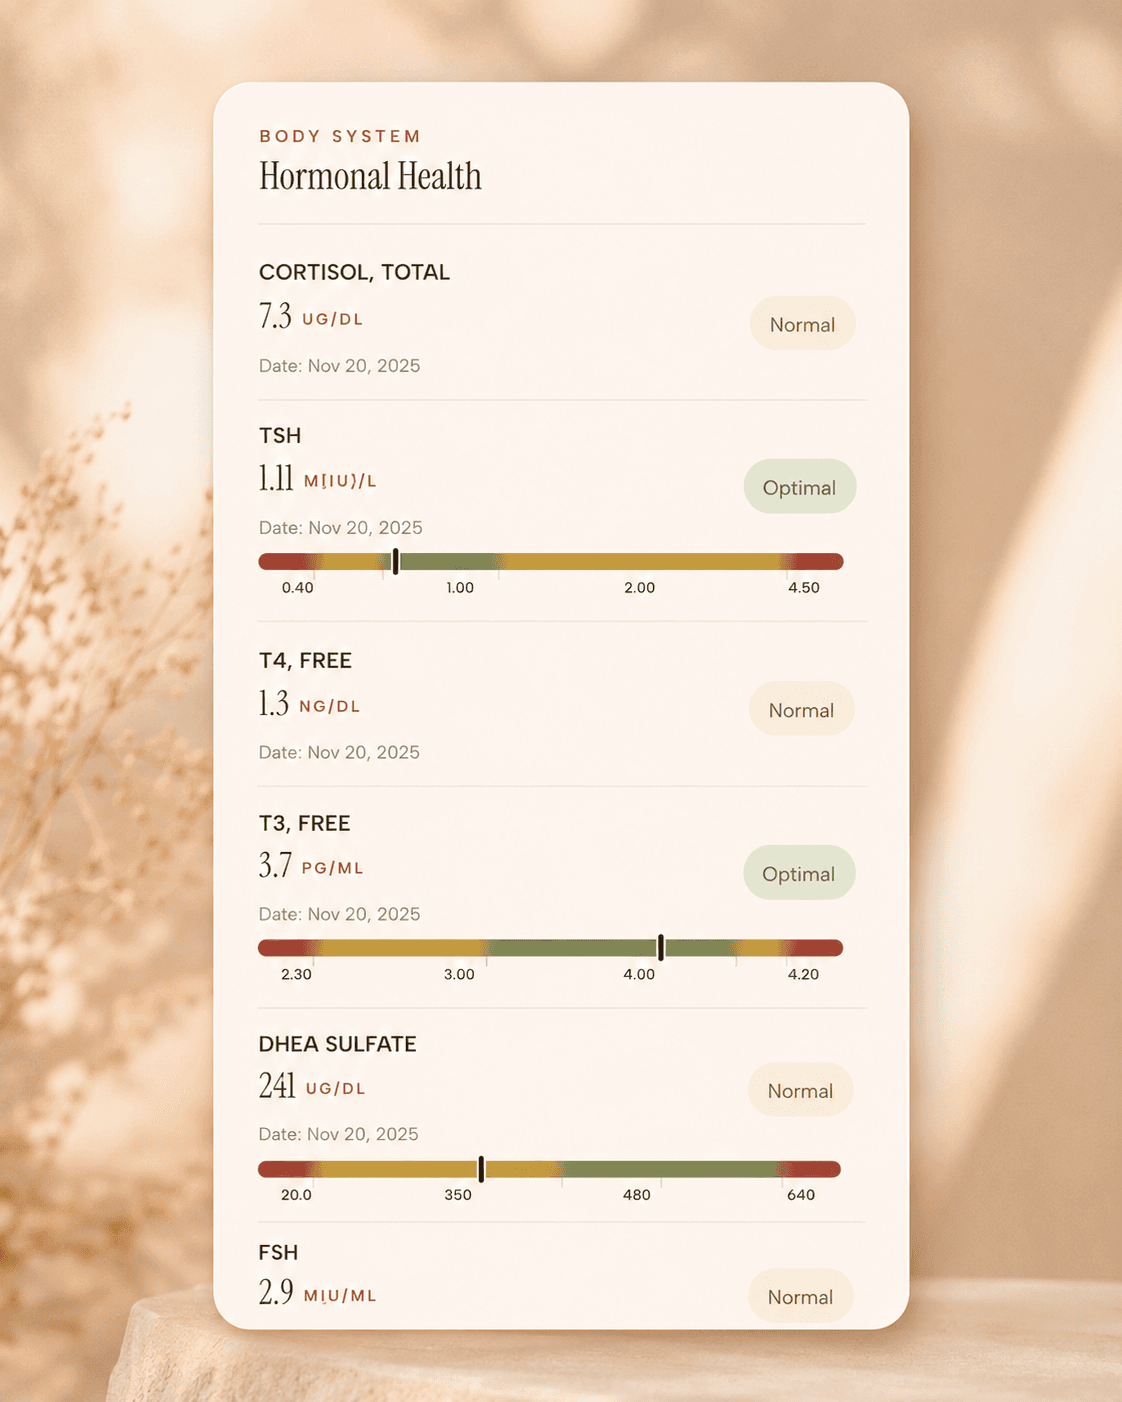
Your estrogen, FSH, thyroid, and metabolic markers can all be checked together. Vitals Vault's starting-from-$99 panel covers 100+ tests in one visit
no referral needed
About 1 week
Schedule online — results typically within a week
Clear next steps
Guidance included, with follow-up care available
HSA / FSA
Eligible for pre-tax health spending accounts
Why This Conversation Is Changing Now
The testosterone analogy is reframing everything
When clinicians ask what medicine would look like if men lost their primary sex hormone at midlife the way women do, the answer is obvious: it would be treated as a major health event with aggressive monitoring and intervention options. Applying that same lens to estrogen loss is helping women and their doctors see perimenopause and menopause as a cardiovascular, neurological, and skeletal risk period — not just a fertility endpoint.
Musculoskeletal pain finally getting connected to hormones
Joint pain, tendon stiffness, and muscle weakness in midlife women have long been dismissed as aging or stress. Emerging research and clinicians like Dr. Gabrielle Lyon are making the case that estrogen plays a direct role in muscle protein synthesis and connective tissue integrity, which means the aching shoulders and creaky knees many women experience in their 40s may have a hormonal explanation — not just a mechanical one.
The Women's Health Initiative shadow is finally lifting
A 2002 study called the Women's Health Initiative [WHI] scared a generation of women and doctors away from hormone therapy after it reported increased breast cancer risk. Subsequent analysis showed the study used older women, a specific synthetic progestin, and oral estrogen — and that the risks were misapplied to all hormone therapy for all women. The medical community is now working to correct that overcorrection, and more women are hearing about it.
How Estrogen Decline Works Inside Your Body
Your brain loses a key neuroprotective signal
Estrogen supports the production of serotonin and dopamine, helps regulate the part of your brain that controls body temperature (the hypothalamus), and appears to protect neurons from inflammation and oxidative damage. When levels drop, many women notice not just hot flashes but also brain fog, mood shifts, disrupted sleep, and a subtle change in how sharp they feel — because those are all downstream effects of losing that neurological support.
Your cardiovascular system loses its natural protection
Before menopause, women have significantly lower rates of heart disease than men of the same age — and estrogen is a major reason why. It helps keep blood vessels flexible, supports healthy cholesterol ratios by raising HDL and lowering LDL, and reduces arterial inflammation. After menopause, women's cardiovascular risk rises sharply and eventually matches or exceeds men's, which is why heart disease — not breast cancer — is the leading cause of death in postmenopausal women.
Bone and muscle begin breaking down faster than they rebuild
Estrogen acts as a brake on the cells that break down bone (osteoclasts), so when estrogen drops, bone loss accelerates dramatically — women can lose up to 20% of their bone density in the five to seven years following menopause. Muscle is affected too, because estrogen supports the body's ability to use protein for muscle repair, meaning the same diet and exercise routine that maintained your muscle at 38 may not be enough at 48.
Who Should Be Paying Attention to This
Women in their late 30s and 40s, not just those near menopause
Perimenopause can begin 8 to 10 years before the final period, and the hormonal fluctuations during that window are often more erratic and symptomatic than menopause itself. If you are in your late 30s and noticing changes in sleep, mood, cycle length, or body composition, your hormones are worth checking — not dismissing as stress.
Women with a family history of heart disease or osteoporosis
Because estrogen decline accelerates both cardiovascular risk and bone loss, women who already carry genetic risk for these conditions face a compounding effect at midlife. Knowing your baseline bone density (via a DEXA scan) and your lipid and inflammatory markers before and during perimenopause gives you and your doctor something concrete to act on.
Women who had surgical menopause or early menopause
If your ovaries were removed before natural menopause, or if menopause arrived before age 45, your body experienced an abrupt estrogen withdrawal rather than a gradual one — and the long-term health risks are proportionally higher. This group in particular has the most to gain from early, informed conversations about hormone therapy and preventive monitoring.
What to Know Before Acting on Any of This
Hormone therapy is not right for everyone
Menopausal hormone therapy [MHT] has a genuinely favorable risk-benefit profile for many healthy women under 60 or within 10 years of menopause — but it is not a universal recommendation. Women with a personal history of certain hormone-sensitive cancers, unexplained vaginal bleeding, or active blood clot disorders need individualized evaluation, not a one-size-fits-all answer from an article or a social media reel.
Symptoms alone cannot tell you what your hormones are doing
Brain fog, fatigue, weight gain, and joint pain have many causes — thyroid dysfunction, iron deficiency, sleep apnea, and depression among them. Assuming everything is estrogen without testing can mean missing something else entirely. A panel that includes estrogen, FSH, thyroid hormones, and metabolic markers gives you an actual picture rather than a guess.
The influencer space moves faster than the evidence does
Some of what you will see online about estrogen — including claims about specific supplement protocols, compounded hormone formulations, or testing methods — is ahead of the clinical evidence. The core science of estrogen's systemic role is solid; the specific product recommendations layered on top of it often are not. Use credentialed clinicians, not comment sections, to make treatment decisions.
Frequently Asked Questions
What age does estrogen decline start in women?
Estrogen levels can begin fluctuating as early as the late 30s, with a more consistent downward trend through the 40s during perimenopause. The sharpest drop happens in the two years around the final menstrual period, but the process is gradual rather than sudden for most women. This is why symptoms often appear years before periods actually stop.
Can low estrogen cause joint pain and muscle aches?
Yes, and this connection is underappreciated in standard care. Estrogen receptors exist in joint tissue and muscle, and declining levels are associated with increased inflammation, reduced muscle protein synthesis, and changes in tendon elasticity. Many women in perimenopause report joint stiffness and new musculoskeletal pain that improves with hormone therapy, though individual responses vary.
Is hormone therapy safe for menopause symptoms?
For most healthy women under 60 who are within 10 years of menopause, the current evidence supports menopausal hormone therapy as safe and effective for managing symptoms and reducing long-term risks like bone loss and cardiovascular disease. Safety depends heavily on individual health history, the type of hormones used, and the route of administration — so this is a conversation to have with a clinician who knows your full picture, not a blanket yes or no.
How do I know if my symptoms are from estrogen decline or something else?
You really cannot tell from symptoms alone, because brain fog, fatigue, weight changes, and mood shifts overlap with thyroid disorders, iron deficiency, sleep apnea, and depression. A blood panel that includes estrogen, FSH, thyroid function, and basic metabolic markers is the most direct way to get clarity. Vitals Vault's panels can check all of these together without a referral.
Does estrogen decline affect heart health in women?
It does, significantly. Estrogen helps maintain flexible blood vessels, supports favorable cholesterol levels, and reduces arterial inflammation — so its loss at menopause is one reason women's cardiovascular risk rises sharply after midlife. Heart disease, not breast cancer, is the leading cause of death in postmenopausal women, which is why cardiovascular monitoring during and after perimenopause is genuinely important.