Medications That Deplete Nutrients: What to Monitor
Yes, some of the most commonly prescribed medications in the world — statins, metformin, acid blockers, and hormonal contraceptives — can gradually reduce your body's levels of specific vitamins and minerals.





Yes, some of the most commonly prescribed medications in the world — statins, metformin, acid blockers, and hormonal contraceptives — can gradually reduce your body's levels of specific vitamins and minerals. This is not a fringe theory; it is a documented pharmacological effect, and the symptoms it causes are often mistaken for the very condition the drug is treating. The tricky part is that nutrient depletion rarely happens overnight. It builds quietly over months or years, which is why fatigue, muscle aches, brain fog, or low mood can feel like your health is just getting worse — when in reality your medication may be part of the picture. If you want to know where you actually stand, a comprehensive blood panel through Vitals Vault or a quick conversation with a PocketMD clinician can help you figure out what to test and what the numbers mean for you.
Why this is trending
Functional medicine physician Mark Hyman published a detailed breakdown this week on how prescription drugs deplete essential nutrients, and it landed hard with a very large, very relatable audience — people on statins for cholesterol, metformin for blood sugar, or the pill for contraception who have been quietly wondering why they still feel off despite being medicated. The post resonated because it named specific drugs and specific nutrients rather than speaking in vague generalities. What is actually new here is not the science — researchers have documented drug-nutrient interactions for decades — but the growing mainstream awareness that standard follow-up care rarely screens for these depletions. Most people are prescribed a medication, told to come back in three months, and never asked whether they are getting enough B12 or magnesium. That gap between what the research shows and what routine care catches is exactly why this conversation is picking up speed.
What Is Drug-Induced Nutrient Depletion?
A documented side effect hiding in plain sight
Drug-induced nutrient depletion happens when a medication interferes with how your body absorbs, uses, or excretes a specific vitamin or mineral. It is listed in the pharmacological literature for dozens of common drugs, but it rarely makes it into the conversation at the pharmacy counter or the follow-up appointment.
Symptoms that mimic your original condition
Because the depletion is gradual, the symptoms — fatigue, muscle weakness, tingling in the hands, low mood, poor memory — tend to look exactly like the condition the drug was prescribed for in the first place. That overlap is why so many people assume they are just getting worse, when a simple blood test might tell a very different story.
Not every patient depletes at the same rate
How quickly a medication affects your nutrient levels depends on your dose, how long you have been taking it, your diet, your age, and whether you have other conditions affecting absorption. Two people on the same statin dose for the same length of time can have very different CoQ10 levels, which is why individual testing matters more than general rules.
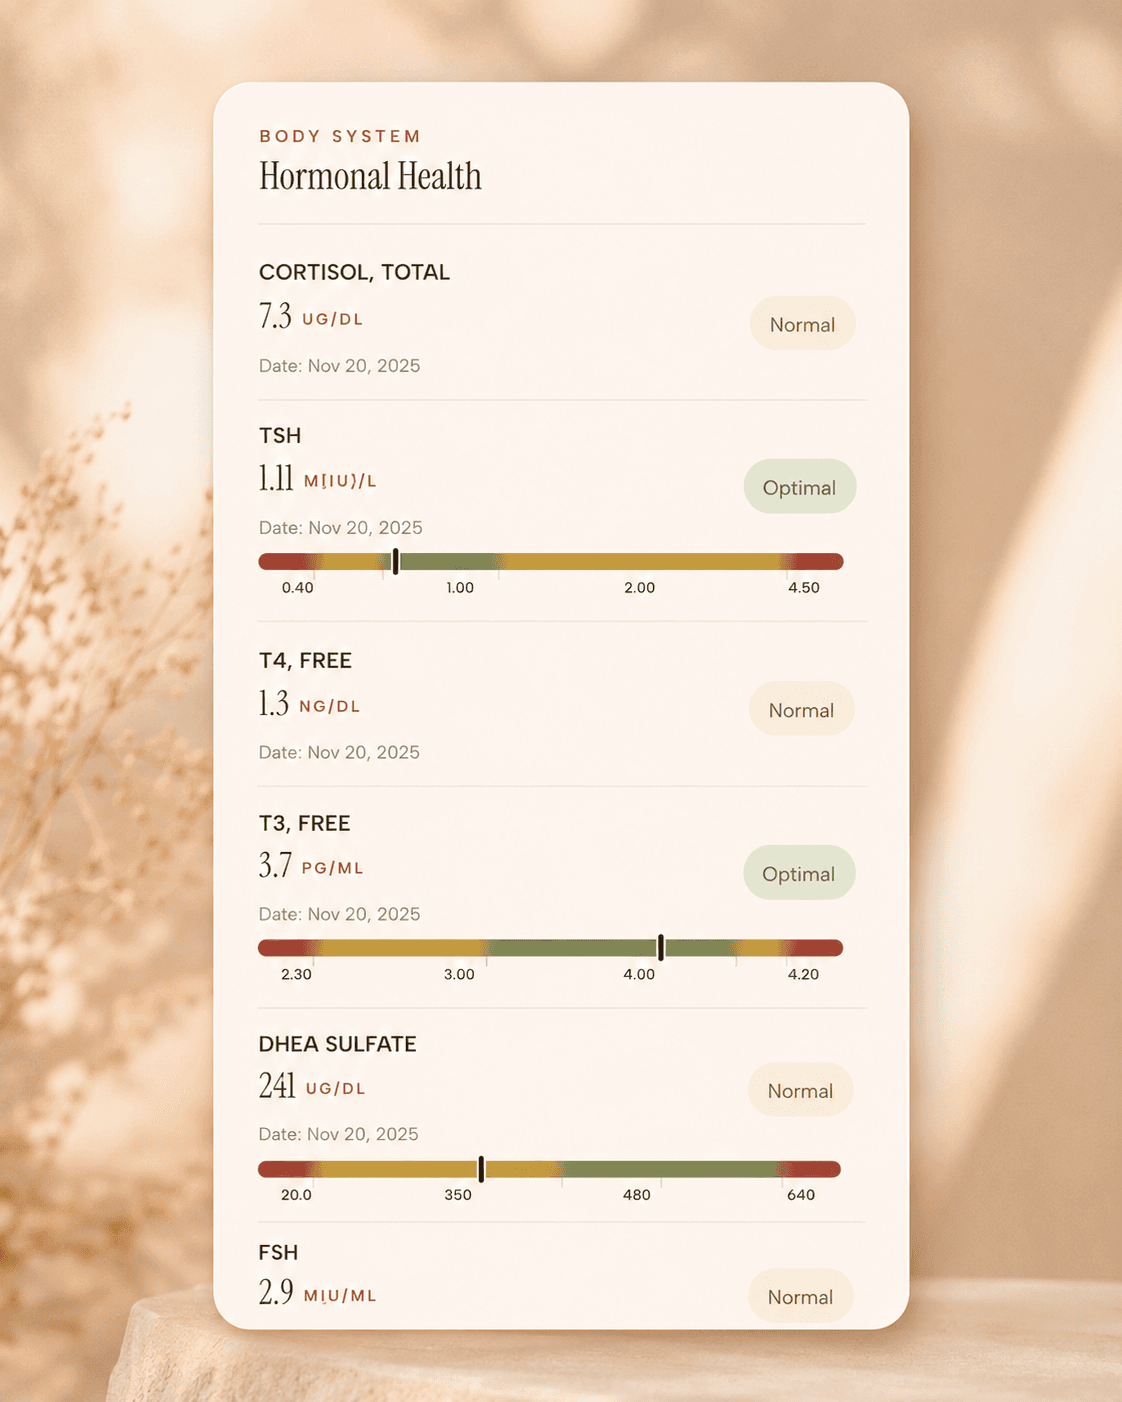
Lab testing
Check the nutrients most commonly depleted by medications
including B12, magnesium, folate, CoQ10, zinc, and vitamin D
with the Vitals Vault starting-from-$99 panel covering 100+ tests, one visit, no referral needed
About 1 week
Schedule online — results typically within a week
Clear next steps
Guidance included, with follow-up care available
HSA / FSA
Eligible for pre-tax health spending accounts
Why This Is Getting Attention Now
Millions of people are on the most depleting drugs
Statins are among the most prescribed medications in the United States, and metformin is not far behind. Add hormonal contraceptives and proton pump inhibitors [PPIs] — the acid-blocking drugs used for reflux — and you have a significant portion of the adult population on medications with well-documented nutrient interactions. When a trusted voice names those drugs specifically, it resonates immediately.
Routine care rarely screens for these gaps
Standard chronic disease management typically tracks the condition being treated — cholesterol numbers, blood sugar, blood pressure — but does not routinely measure the nutrients that the treatment may be depleting. That means a person could be on metformin for years with a falling B12 level and never be told until nerve symptoms appear.
People are connecting their own dots
Online health communities are full of people who started a new medication and noticed fatigue or brain fog a few months later, then found their way to research on drug-nutrient interactions and felt, for the first time, that someone had explained what was happening to them. That pattern of self-discovery is driving the search volume and the social media conversation right now.
How These Drugs Actually Deplete Nutrients
Statins and the CoQ10 connection
Statins work by blocking an enzyme [HMG-CoA reductase] that your liver uses to make cholesterol — but that same pathway also produces coenzyme Q10 [CoQ10], a compound your muscle cells rely on to generate energy. When CoQ10 drops, the muscle aches and fatigue that some statin users experience may not be a coincidence, though the evidence on whether supplementing CoQ10 reliably fixes those symptoms is still mixed.
Metformin and vitamin B12 absorption
Metformin, the first-line drug for type 2 diabetes, reduces how well your gut absorbs vitamin B12 — and it does this more significantly the longer you take it and the higher the dose. Low B12 causes symptoms like tingling in the feet, fatigue, and memory problems that are easy to attribute to diabetes itself, which is why the American Diabetes Association now recommends periodic B12 monitoring for anyone on long-term metformin.
Hormonal contraceptives and the B-vitamin cascade
The estrogen in combined hormonal contraceptives affects how your body processes several B vitamins — particularly B6, B12, folate, and riboflavin — as well as zinc and magnesium. The effect is not dramatic enough to cause obvious deficiency in most healthy young women eating a varied diet, but for someone already eating low in these nutrients or under chronic stress, the pill can tip the balance toward symptoms like low mood, poor sleep, and reduced energy.
PPIs and the mineral problem
Proton pump inhibitors reduce stomach acid dramatically, which is exactly what they are designed to do for reflux — but stomach acid is also how your body releases and absorbs magnesium, calcium, iron, and B12 from food. Long-term PPI use is associated with low magnesium levels [hypomagnesemia], which can cause muscle cramps, irregular heartbeat, and anxiety, and the FDA has issued a safety communication about this risk specifically.
Who Should Pay Closest Attention
Anyone on these medications for more than a year
Short-term use of most of these drugs carries a much lower depletion risk than long-term use, because the body can compensate for a while. If you have been on a statin, metformin, a PPI, or hormonal contraceptives for more than 12 months and have noticed new fatigue, muscle issues, or mood changes, it is worth asking your doctor whether your nutrient levels have been checked recently.
Older adults on multiple medications
Nutrient absorption naturally becomes less efficient as you age, and many older adults are on several medications simultaneously — a statin, a blood pressure drug, and a PPI, for example — each of which may have its own depletion effect. The combined impact can be significant, and because the symptoms overlap with normal aging, they are frequently dismissed rather than investigated.
People with diets already low in key nutrients
If your diet is already low in animal protein — the main dietary source of B12 — or you avoid dairy and fortified foods, a medication that further reduces B12 absorption can push you into deficiency much faster than it would someone eating a nutrient-dense diet. Your baseline intake matters enormously when assessing your personal risk.
What to Watch Out For Before You Change Anything
Do not stop your medication based on this information
The nutrients these drugs deplete are important, but so are the conditions the drugs are treating. Stopping a statin or metformin without medical guidance can carry real cardiovascular or metabolic risks that outweigh the nutrient concern. The right move is to get tested, bring the results to your prescriber, and have a conversation about whether supplementing makes sense — not to make a unilateral decision.
Supplements are not automatically safe or effective
Some supplements interact with medications — for example, high-dose magnesium can affect how certain heart medications work, and iron supplements can reduce the absorption of some drugs if taken at the same time. Supplementing without knowing your actual levels also means you might be adding something you do not need, which carries its own risks for fat-soluble vitamins like D and A.
The evidence on some depletions is stronger than others
The B12-metformin link and the magnesium-PPI link are well-established and recognized by major medical organizations. The CoQ10-statin connection is real at the biochemical level, but whether supplementing CoQ10 reliably reduces statin-related muscle symptoms is still debated in the research literature. Be appropriately skeptical of anyone who presents all drug-nutrient interactions as equally proven — they are not.
Frequently Asked Questions
Does everyone who takes a statin get low CoQ10?
Statins do reduce CoQ10 levels in the blood in most people who take them, but how much that matters clinically varies a great deal from person to person. Some people on statins feel completely fine; others notice muscle fatigue or weakness that may be related to the drop in CoQ10. Testing your levels and discussing the results with your doctor is a more useful approach than assuming you either do or do not have a problem.
How long does it take for metformin to lower B12 levels?
Research suggests that meaningful B12 decline can begin within one to two years of starting metformin, and the risk increases with higher doses and longer duration of use. Because B12 is stored in the liver, you can have depleted absorption for quite a while before your blood levels fall low enough to cause symptoms — which is exactly why periodic testing rather than waiting for symptoms is the recommended approach.
Can I just take a multivitamin to cover all my bases while on these medications?
A multivitamin can help fill dietary gaps, but it is not a reliable solution for drug-induced depletion because the doses of specific nutrients in most multivitamins are too low to compensate for ongoing medication-driven losses. For example, the B12 in a standard multivitamin is unlikely to be enough for someone on long-term high-dose metformin with documented low levels. Targeted supplementation based on actual test results is a more precise approach.
Are there blood tests specifically for drug-induced nutrient depletion?
There is no single test called a drug-nutrient depletion panel, but the individual nutrients involved — B12, folate, magnesium, zinc, vitamin D, and others — are all measurable through standard blood work. Vitals Vault's comprehensive panel covers more than 100 markers including many of these, which gives you a clear picture of where you actually stand rather than guessing based on symptoms alone.
Do blood pressure medications also deplete nutrients?
Some do. Thiazide diuretics — a common class of blood pressure medication — increase how much magnesium and potassium your kidneys excrete, which can lead to low levels of both over time. Low potassium can cause muscle weakness and heart rhythm irregularities, and low magnesium can worsen blood pressure control — a somewhat ironic outcome for a blood pressure drug. If you are on a diuretic, it is worth asking your doctor whether your electrolytes are being monitored regularly.