ADHD & Menopause Overlap: Why Women Are Diagnosed Late
If you sailed through your 30s and then suddenly found yourself unable to finish a sentence, losing your keys three times before noon, and crying in a parking lot over nothing — you are not imagining things, and you are not alone.



If you sailed through your 30s and then suddenly found yourself unable to finish a sentence, losing your keys three times before noon, and crying in a parking lot over nothing — you are not imagining things, and you are not alone. For a significant number of women, perimenopause does not just bring hot flashes; it pulls back a curtain on attention and emotional regulation struggles that were always there but quietly managed. That is the ADHD-menopause overlap, and it is finally getting the clinical attention it deserves. For decades, ADHD research was built almost entirely on data from boys and men, which means millions of women learned to cope, compensate, and mask their symptoms so effectively that no one — including their doctors — ever flagged them. Then estrogen starts to drop in the mid-to-late 40s, and the coping strategies that held everything together begin to fail. If you want to understand what your labs might be telling you about your hormones and neurotransmitters, Vitals Vault's starting-from-$99 panel and PocketMD telehealth line are there when you need a starting point.
Why this is trending
This conversation has been building in women's health spaces for a few years, but it reached a new level of visibility recently when Dr. Mary Claire Haver — one of the most-followed menopause physicians on social media — published multiple videos and a full episode with psychiatrist Dr. Sasha Hamdani specifically on the ADHD-menopause connection. Their discussion brought clinical nuance to an audience of millions who had been quietly wondering whether their perimenopausal brain fog was something more. What is genuinely new here is not the existence of the overlap — researchers have suspected it for years — but the growing body of evidence linking estrogen's role in brain chemistry to attention and impulse control. Clinicians are starting to take late-diagnosis ADHD in women seriously rather than dismissing it as anxiety or depression. That shift in medical culture, combined with louder patient voices online, is why this topic is landing in so many feeds right now.
What This Overlap Actually Is
Two conditions that share a symptom language
ADHD and perimenopause both produce brain fog, emotional volatility, poor working memory, and difficulty sustaining attention — which means they are genuinely hard to tell apart without a careful history. What makes it more complicated is that they can exist at the same time, each making the other worse.
A diagnosis that was missed the first time around
Many women who receive an ADHD diagnosis in their 40s actually had it their whole lives, but their symptoms were attributed to anxiety, being "sensitive," or just not trying hard enough. The hormonal stability of their reproductive years gave them just enough neurochemical buffer to keep things functional — until perimenopause removed that buffer.
Not a new disorder, but a newly visible one
Getting diagnosed at 44 does not mean you developed ADHD at 44. It means the conditions that were masking it finally changed. Understanding this distinction matters because it shapes the treatment approach — you are managing a lifelong neurological pattern that has been newly destabilized, not a brand-new psychiatric condition.
Lab testing
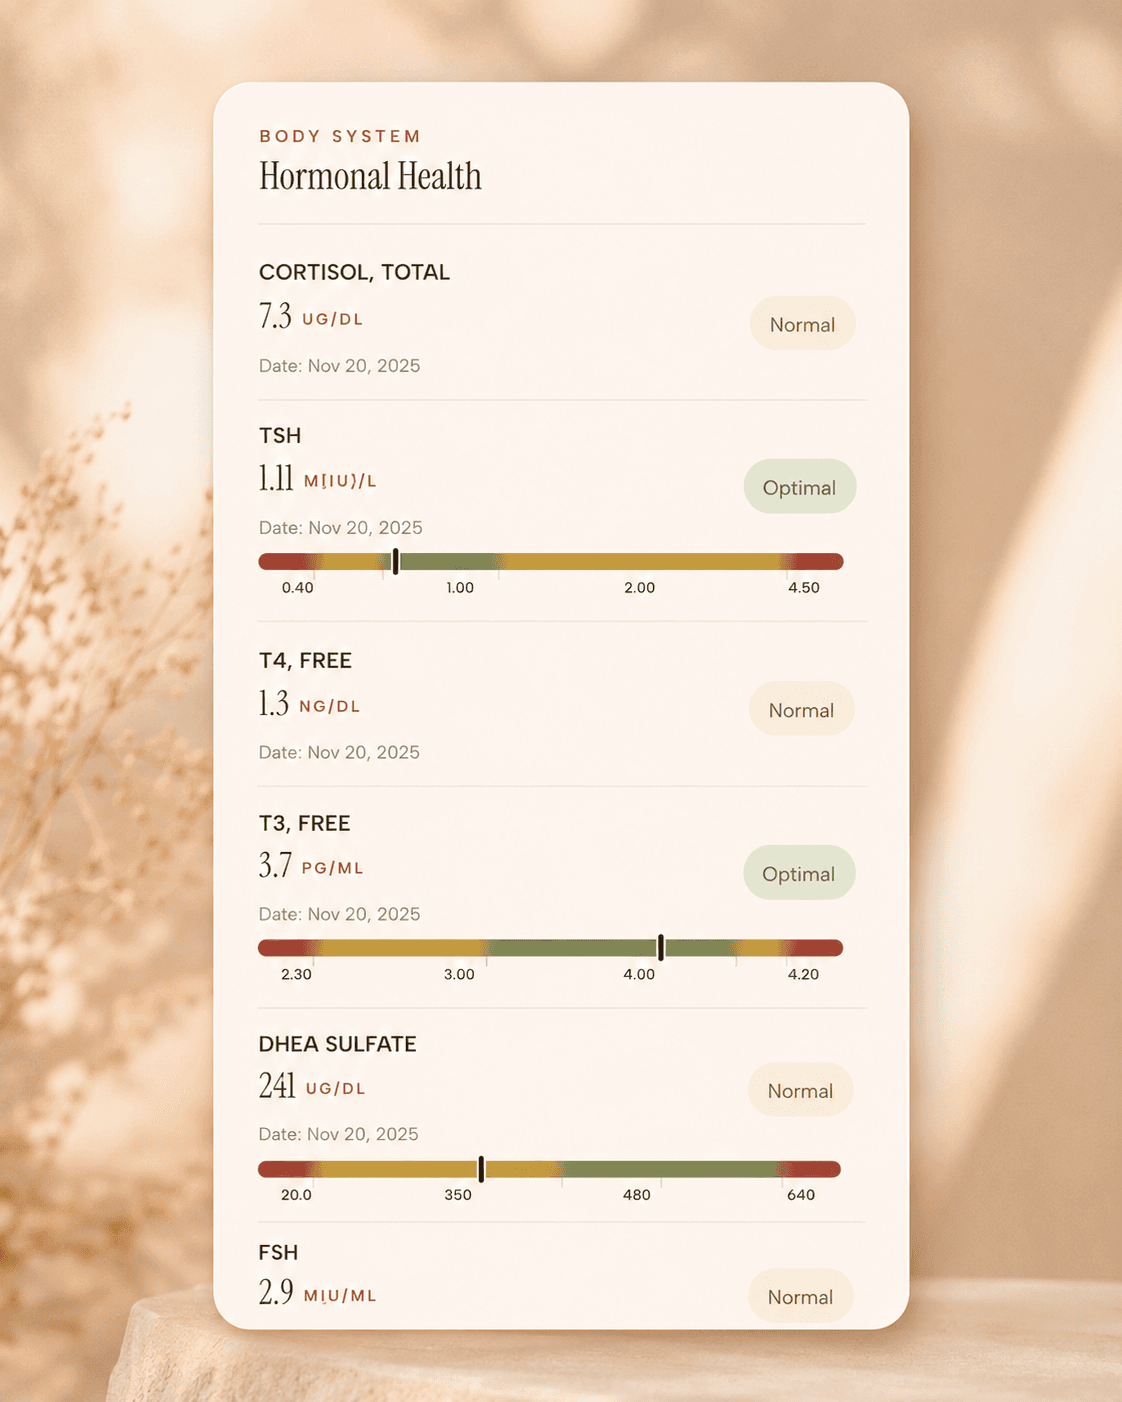
Your estrogen, thyroid, and cortisol levels can all influence focus and mood
and they're measurable
The Vitals Vault starting-from-$99 panel covers 100+ markers in one visit, so you can walk into any conversation with your doctor already knowing your numbers
About 1 week
Schedule online — results typically within a week
Clear next steps
Guidance included, with follow-up care available
HSA / FSA
Eligible for pre-tax health spending accounts
Why This Is Trending Now
Clinicians are finally listening to women's reports
For years, women who described attention problems during perimenopause were often told it was just stress or depression. A growing number of psychiatrists and gynecologists are now recognizing that these reports deserve a proper ADHD evaluation rather than a reflexive antidepressant prescription.
Social media is connecting isolated experiences
Women who spent decades thinking they were uniquely disorganized or emotionally fragile are finding each other online and recognizing a shared pattern. That collective recognition is pushing the conversation into clinical spaces in a way that individual patient reports never could.
The research base is finally catching up
Studies on estrogen's role in dopamine regulation have existed for years, but they were largely siloed in neuroscience journals rather than reaching gynecologists or psychiatrists. Cross-specialty collaboration is now producing clinical guidance that treats the brain as part of the menopausal transition — not a separate issue.
How the Biology Works
Estrogen keeps your dopamine system running smoothly
Estrogen does not just govern your reproductive cycle — it actively supports the brain's dopamine system, which controls motivation, focus, and the ability to filter out distractions. When estrogen levels are stable, your brain has a reliable scaffold for attention; when they start fluctuating and falling during perimenopause, that scaffold wobbles.
ADHD is already a dopamine and norepinephrine problem
The core of ADHD involves the brain's difficulty regulating two chemical messengers: dopamine and norepinephrine [a signaling molecule that governs alertness and working memory]. If your brain was already running lean on these chemicals, losing estrogen's supporting role is like losing a crutch you did not know you were leaning on.
The prefrontal cortex takes the biggest hit
The front part of your brain [prefrontal cortex] handles planning, impulse control, and emotional regulation — and it is both the primary site of ADHD-related dysfunction and one of the brain regions most sensitive to estrogen changes. This is why perimenopausal women with undiagnosed ADHD often describe a sudden collapse in their ability to manage emotions and stay organized, rather than a gradual decline.
Who Should Pay Attention
Women in their 40s whose coping strategies stopped working
If you were always a little scattered but managed fine, and then somewhere in your 40s everything fell apart — the calendar system stopped helping, the to-do lists stopped working, the emotional reactions started feeling out of proportion — that pattern is worth discussing with a clinician who understands both ADHD and perimenopause.
Women already diagnosed with ADHD who feel their meds stopped working
If your stimulant medication worked reliably for years and then seemed to lose its effect without any obvious reason, falling estrogen is a plausible explanation. Some women find that addressing the hormonal side of the equation restores the medication's effectiveness, though this is highly individual and needs medical supervision.
Women told they have anxiety or depression that never quite fit
ADHD in women is frequently misdiagnosed as generalized anxiety or depression because the emotional dysregulation and overwhelm look similar on the surface. If you have been treated for those conditions without feeling like the diagnosis ever fully explained your experience, an ADHD evaluation during perimenopause may finally provide a clearer picture.
Risks and Caveats
Self-diagnosis from a social media video is not a diagnosis
Recognizing yourself in a description of ADHD-menopause overlap is a useful starting point, but it is not the same as a clinical evaluation. Thyroid dysfunction, sleep apnea, and chronic stress can all produce nearly identical symptoms, so a proper workup — including labs — matters before anyone starts a new treatment.
Hormone therapy and ADHD medication interact in ways that need monitoring
Some women find that menopausal hormone therapy improves their attention symptoms enough that stimulant doses need to be adjusted. Starting or changing either treatment without telling both your prescribing clinicians creates real risk, so make sure everyone involved in your care knows the full picture.
Not every perimenopausal woman with brain fog has ADHD
The overlap is real, but it is not universal — and treating ADHD that is not actually there carries its own risks, particularly with stimulant medications. The goal is an accurate diagnosis, not a trendy one, which is why a thorough evaluation by a clinician familiar with both conditions is worth the effort.
Frequently Asked Questions
Can perimenopause actually cause ADHD, or does it just make existing ADHD worse?
Perimenopause does not create ADHD from scratch — ADHD is a neurodevelopmental condition that is present from childhood. What perimenopause can do is remove the hormonal support that was quietly compensating for it, making symptoms appear or intensify in a way that finally crosses the threshold for diagnosis. Think of it as the condition being unmasked rather than newly created.
Why were so many women with ADHD never diagnosed as children?
ADHD research and diagnostic criteria were built almost entirely on studies of boys, whose ADHD tends to look hyperactive and disruptive. Girls with ADHD more often internalize their struggles — daydreaming, people-pleasing, and working twice as hard to appear organized — which means teachers and doctors rarely flagged them. By adulthood, many had developed such effective masking strategies that the underlying condition stayed invisible.
What does ADHD rage have to do with menopause?
Emotional dysregulation — including intense, fast-rising anger that feels disproportionate to the situation — is a recognized feature of ADHD, not just a personality quirk. Estrogen normally helps buffer emotional reactivity, so when it drops during perimenopause, women with ADHD (diagnosed or not) can experience a significant worsening of emotional intensity. Addressing both the hormonal and the neurological sides of the equation tends to help more than treating either one alone.
Will hormone therapy fix my ADHD symptoms?
For some women, menopausal hormone therapy improves attention and emotional regulation noticeably — because it restores some of the estrogen support that the dopamine system lost. But hormone therapy is not an ADHD treatment, and it does not work the same way for everyone. Some women still need ADHD-specific treatment alongside it, and the right combination depends on your individual history and lab values.
How do I bring this up with a doctor who might not take it seriously?
Come prepared with a timeline: when your symptoms started or worsened, how they affect specific daily tasks, and whether you recognize similar patterns from earlier in your life. Asking for a referral to a psychiatrist who works with adult women, or a gynecologist who specializes in menopause, gives you a better chance of being heard than a general practitioner who may not be familiar with the overlap. If you want to go in with your hormone and thyroid numbers already in hand, a Vitals Vault lab panel can give you that foundation before the appointment.